DAP Notes: How to Write Them, With 7 Examples & a Template
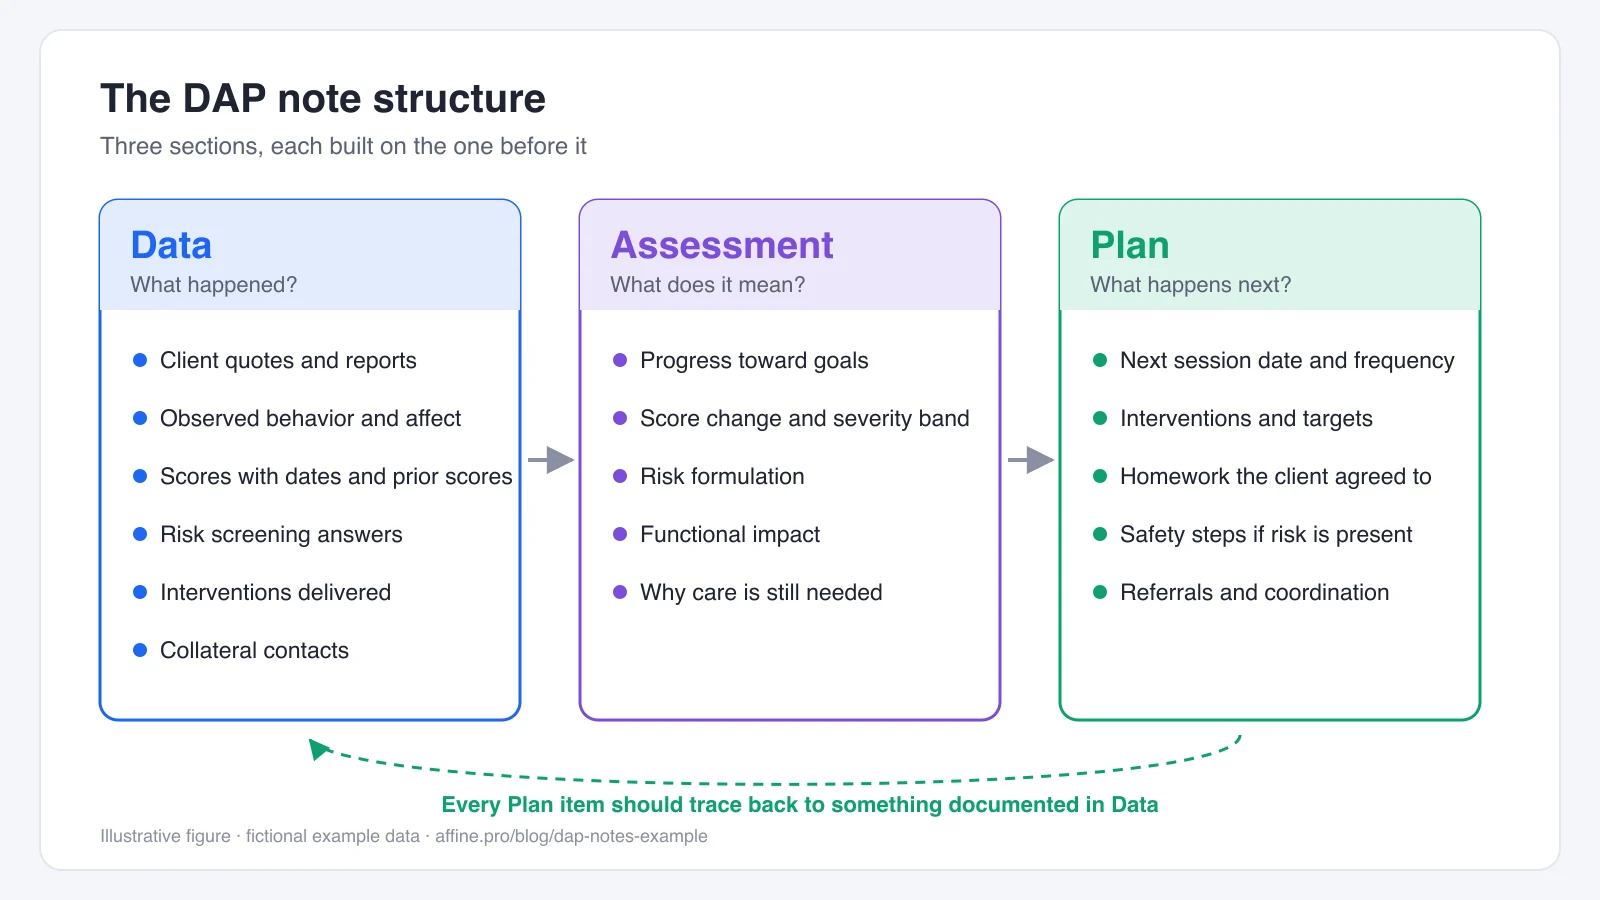
A DAP note is a three-part therapy progress note: Data, Assessment, and Plan. Data records what the client said and what you observed or measured in the session. Assessment explains what that information means clinically. Plan lists what happens next and why. Each section should follow from the one before it, so a reviewer can trace every plan item back to a documented fact.
This guide is for counselors, therapists, social workers, case managers, and students who write progress notes in behavioral health. It covers a complete DAP note example, how to write each section, six more examples for common session types, a copy-ready template, and an audit checklist. It is a documentation guide, not clinical, legal, or billing advice. Your employer, payers, state licensing board, and EHR policy set the rules you have to follow.
DAP notes at a glance
| Section | Question it answers | Include | Leave out |
|---|---|---|---|
| Data | What happened in the session? | Client quotes, observed behavior, mental status, scores, risk screening, interventions delivered | Your interpretation, diagnoses, labels such as "manipulative" or "safe" |
| Assessment | What does it mean? | Progress toward goals, symptom change, score interpretation, risk formulation, functional impact | New facts that are not in Data, judgmental language |
| Plan | What happens next? | Next session, interventions, homework, goal targets, safety steps, referrals and coordination | Vague lines such as "continue therapy" with no detail |
A DAP note is shorter than a SOAP note because client reports and clinician observations share one Data section instead of being split into Subjective and Objective. That makes DAP popular for ongoing therapy and counseling sessions, where the session content is mostly conversation and behavior rather than vitals or lab results.
A complete DAP note example
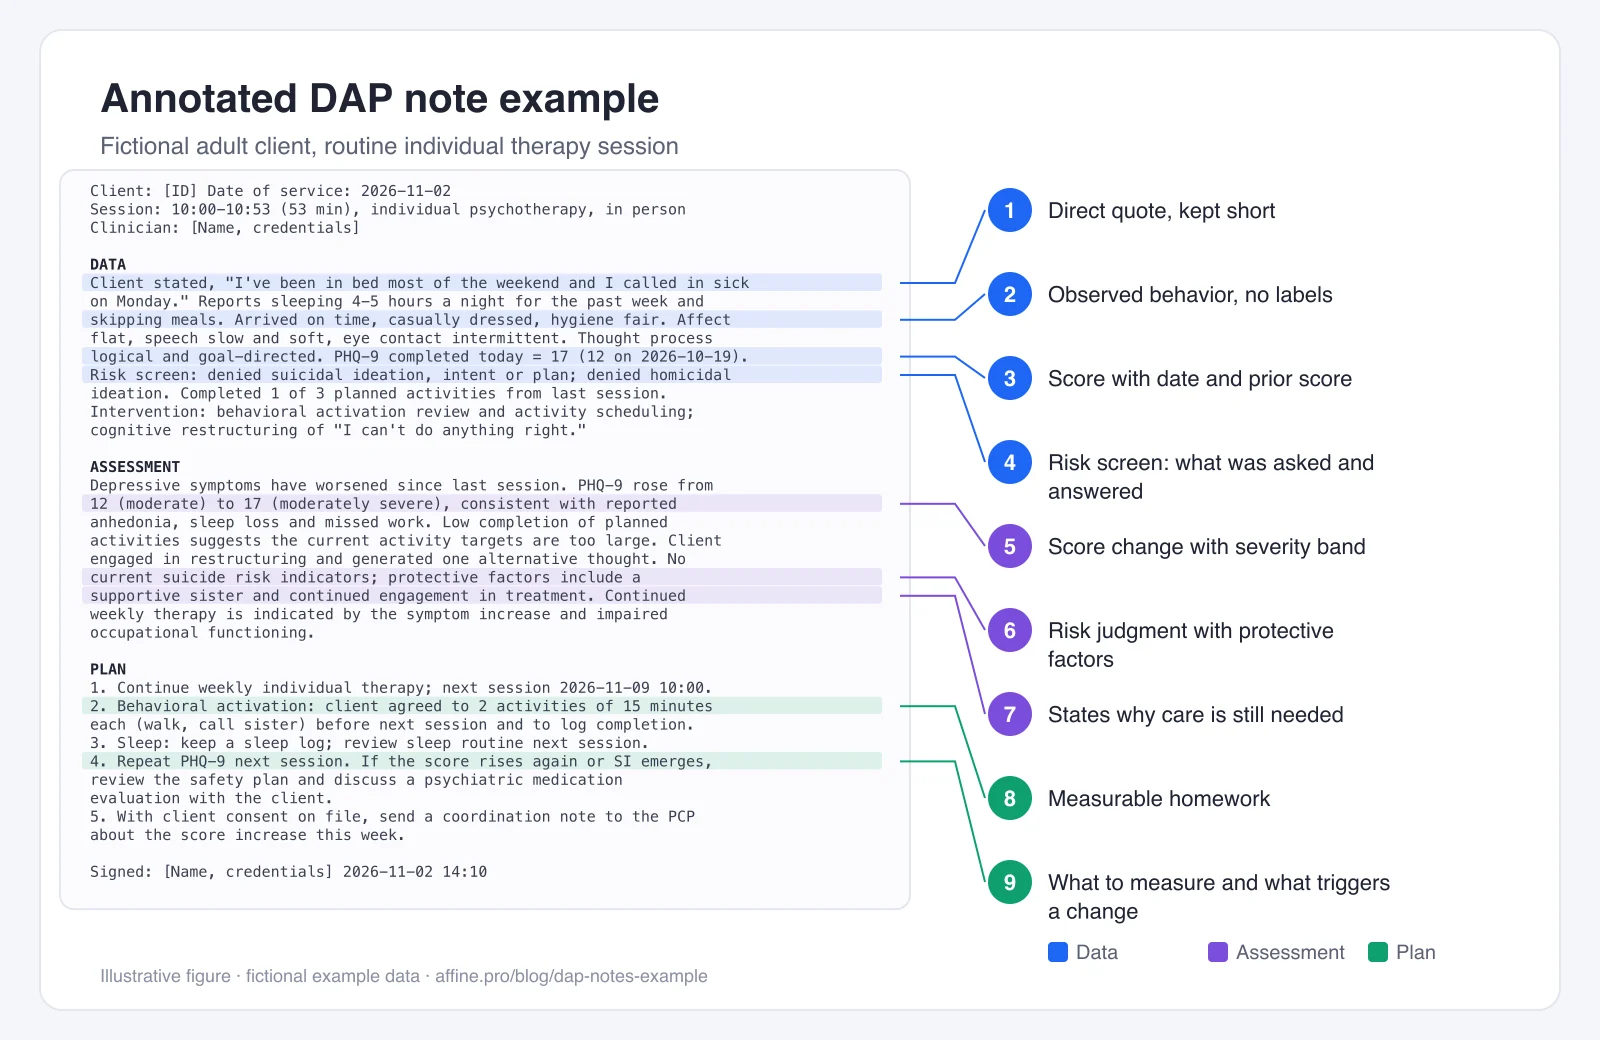
The example below is fictional. It shows a routine individual therapy session for an adult client being treated for depression. Every Assessment statement points back to something in Data, and every Plan item answers something in Assessment.
Client: [ID]          Date of service: 2026-11-02
Session: 10:00-10:53 (53 min), individual psychotherapy, in person
Clinician: [Name, credentials]

DATA
Client stated, "I've been in bed most of the weekend and I called in sick
on Monday." Reports sleeping 4-5 hours a night for the past week and
skipping meals. Arrived on time, casually dressed, hygiene fair. Affect
flat, speech slow and soft, eye contact intermittent. Thought process
logical and goal-directed. PHQ-9 completed today = 17 (12 on 2026-10-19).
Risk screen: denied suicidal ideation, intent or plan; denied homicidal
ideation. Completed 1 of 3 planned activities from last session.
Intervention: behavioral activation review and activity scheduling;
cognitive restructuring of "I can't do anything right."

ASSESSMENT
Depressive symptoms have worsened since last session. PHQ-9 rose from
12 (moderate) to 17 (moderately severe), consistent with reported
anhedonia, sleep loss and missed work. Low completion of planned
activities suggests the current activity targets are too large. Client
engaged in restructuring and generated one alternative thought. No
current suicide risk indicators; protective factors include a
supportive sister and continued engagement in treatment. Continued
weekly therapy is indicated by the symptom increase and impaired
occupational functioning.

PLAN
1. Continue weekly individual therapy; next session 2026-11-09 10:00.
2. Behavioral activation: client agreed to 2 activities of 15 minutes
   each (walk, call sister) before next session and to log completion.
3. Sleep: keep a sleep log; review sleep routine next session.
4. Repeat PHQ-9 next session. If the score rises again or SI emerges,
   review the safety plan and discuss a psychiatric medication
   evaluation with the client.
5. With client consent on file, send a coordination note to the PCP
   about the score increase this week.

Signed: [Name, credentials]    2026-11-02 14:10
Why this example works:
- Data stays factual. It quotes the client, describes behavior a second clinician would also see, and records the PHQ-9 score with its date and the prior score.
- Assessment interprets, it does not add facts. The PHQ-9 change, missed work and low activity completion all appear in Data first.
- Plan is specific. Another clinician could pick up this note and know the next session date, the homework, what to measure and what would trigger a change.
- The note says why care continues. The last Assessment sentence links continued weekly therapy to symptoms and functional impairment, which is what a reviewer looks for when checking medical necessity.
How to write a DAP note, step by step
Step 1: Fill in the session header
The header is the part of a progress note most often checked in audits, and it is easy to get right. Most organizations and payers expect these fields on every note:
| Field | Example | Why it matters |
|---|---|---|
| Client identifier | Name or record ID, date of birth | Ties the note to the right record |
| Date of service | 2026-11-02 | Matches the claim and the schedule |
| Start and stop time | 10:00-10:53 (53 min) | Time-based psychotherapy codes depend on it |
| Service type and setting | Individual psychotherapy, in person or telehealth | Matches the service that was billed |
| Participants | Client only, or client and parent | Shows who was present for family or collateral work |
| Clinician and signature | Name, credentials, date and time signed | Authenticates the note |
For telehealth sessions, add a short line such as "Telehealth via [platform], audio and video. Consent on file. Client located at [city, state]; clinician at [city, state]. Emergency contact and location confirmed." Telehealth rules vary by payer and state, so check which of these items yours require. CMS updates the list of Medicare telehealth services every year.
Step 2: Write the Data section
Data is the factual record of the session. A useful test: could a second clinician who was in the room agree with every sentence? If a sentence needs your judgment, it belongs in Assessment.
Data usually includes:
- What the client said. Short, relevant quotes, or a summary such as "Client reported…".
- What you observed. Appearance, behavior, affect, speech, thought process and engagement.
- Measures. Instrument name, score, date, and the prior score if there is one.
- Risk screening. Exactly what was asked and answered, for example "Denied SI, intent or plan."
- What you did. The interventions delivered in the session.
- Collateral and required reports. Who you contacted, when, and why.
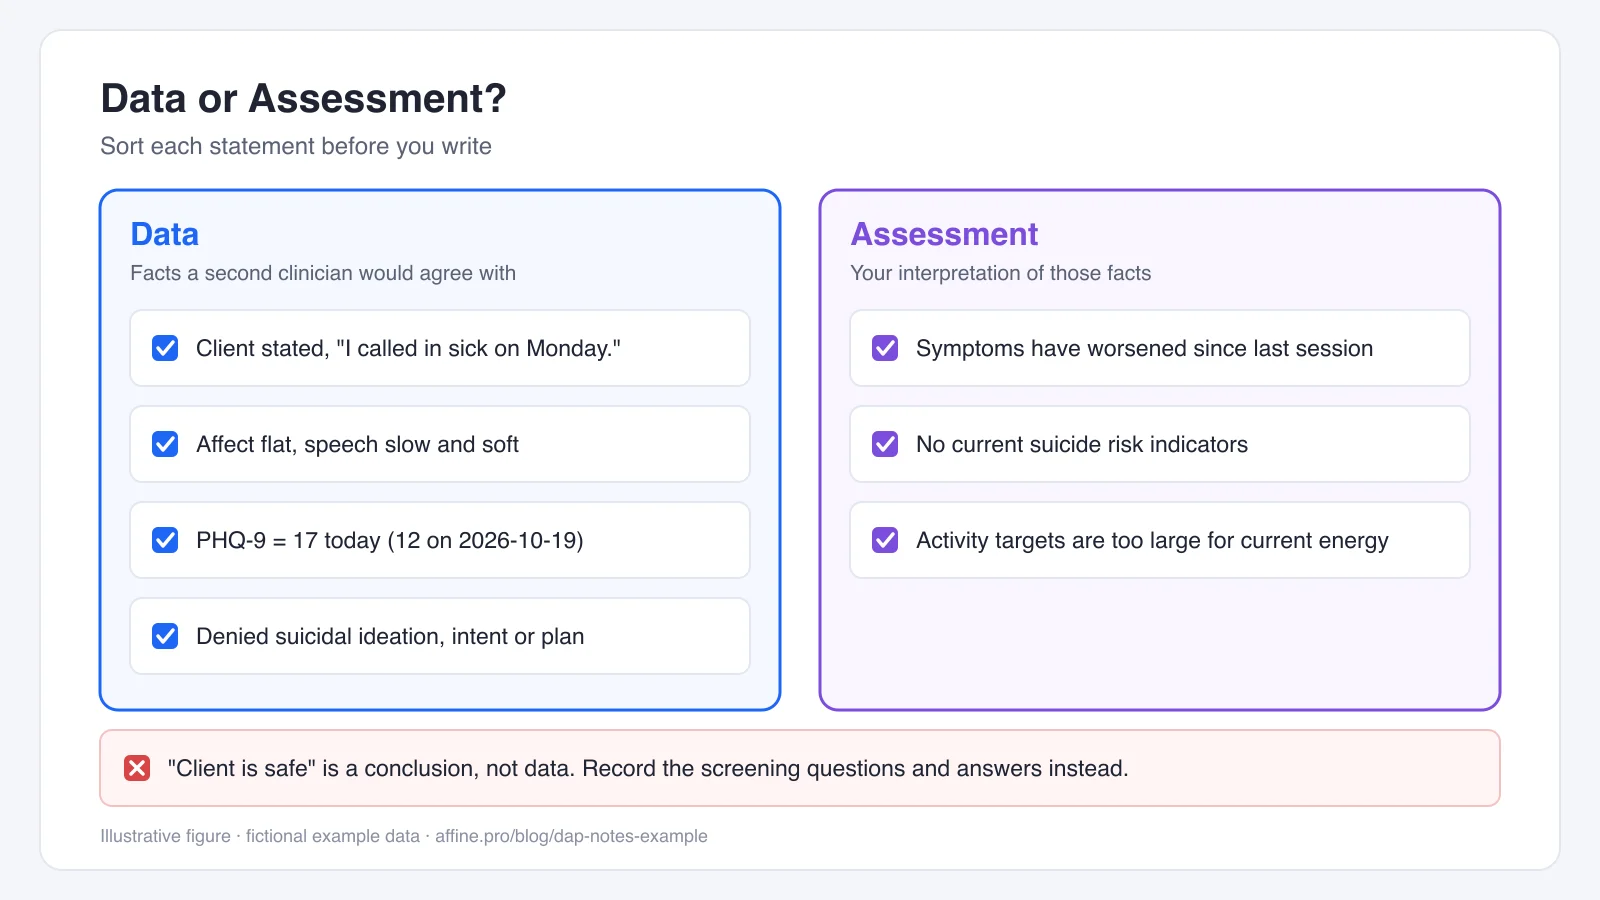
Vague wording is the most common Data problem. Replace labels with what you saw or heard:
| Instead of | Write |
|---|---|
| Client seemed anxious. | Client fidgeted throughout session, speech rapid, reported "my chest gets tight before meetings." |
| Client was sad. | Client was tearful when discussing her father's death; affect constricted. |
| Client is safe. | Denied suicidal ideation, intent or plan; denied homicidal ideation. |
| Client was manipulative. | Client asked three times to end the session early and changed topic when homework was raised. |
| Client did well. | Client completed 3 of 3 planned exposures and rated peak anxiety 6/10, down from 8/10. |
Step 3: Write the Assessment section
Assessment is where you show clinical reasoning. Tie each statement to the Data above it, and cover four things:
- Progress. Is the client improving, worse, or unchanged on the treatment goals, and what in Data shows that?
- Measures. What does the score mean, and how has it moved?
- Risk. What is the current risk, and what are the risk and protective factors behind that judgment?
- Need for care. Why the current level and frequency of treatment are still needed, given symptoms and functioning.
Standardized measures are easier to interpret when you state the severity band. The common cut points come from the original validation studies:
| Measure | Score range | Severity bands | Source |
|---|---|---|---|
| PHQ-9 (depression) | 0-27 | 5 mild, 10 moderate, 15 moderately severe, 20 severe | Kroenke, Spitzer and Williams, 2001 |
| GAD-7 (anxiety) | 0-21 | 5 mild, 10 moderate, 15 severe | Spitzer et al., 2006 |
Example Assessment lines:
- "GAD-7 decreased from 15 (severe) to 11 (moderate) after four weeks of exposure practice; client reports attending two team meetings she previously avoided."
- "No change in PHQ-9 (14 to 14) over three sessions; will review the treatment plan with the client next session."
For risk, write a short formulation instead of a one-word rating: what the client reported, the risk factors, the protective factors, and your judgment. For example: "Passive death wish twice this week without intent or plan; no past attempts. Protective factors: lives with partner, future-oriented about daughter's graduation, engaged in treatment. Risk assessed as low to moderate; safety plan reviewed." Use the risk tool and levels your organization requires.
Step 4: Write the Plan section
The Plan turns the Assessment into actions. A good test is whether a covering clinician could carry it out without calling you. Include:
- Next contact. Frequency and the date and time of the next session.
- Interventions and goals. The methods you will use, tied to a measurable target such as "PHQ-9 below 10 within eight weeks."
- Homework. Specific tasks the client agreed to, so you can check them next session.
- Safety steps. If risk was present, what was reviewed, updated or provided.
- Coordination and referrals. Who you will contact and why, with consent noted.
Avoid ending the Plan with "continue current treatment" alone. If treatment continues unchanged, say what continues and why.
More DAP note examples
All six examples are fictional. They are written to show structure, not to set clinical standards for any client.
Example 2: Generalized anxiety, telehealth session
DATA
Telehealth via [platform], audio and video; consent on file; client at
home in [city, state], clinician in [city, state]. Client stated, "I
went to both meetings this week, but I rehearsed every sentence the
night before." Reports 2 nights of sleep under 5 hours. Speech rapid,
frequent hand-wringing visible on camera. GAD-7 today = 11 (15 on
2026-10-05). Denied SI/HI. Intervention: reviewed worry log;
introduced scheduled worry time.

ASSESSMENT
Anxiety symptoms are improving. GAD-7 moved from severe to moderate
range and client is attending meetings she previously avoided.
Rehearsal and short sleep suggest anticipatory worry is still high.
No current risk indicators.

PLAN
Weekly telehealth; next session 2026-11-10 17:00. Practice scheduled
worry time daily for 15 minutes and log it. Repeat GAD-7 in two weeks.
Target: GAD-7 below 10 by 2026-12-15.
Example 3: Suicide risk reviewed and safety plan updated
DATA
Client stated, "Some nights I think everyone would be better off
without me." Reports this thought 3 times in the past week, most
recently 2026-11-01, lasting minutes. Denied intent or plan. Denied
access to firearms; reports medications are kept by partner. No past
attempts. PHQ-9 = 19; item 9 scored 2. Affect tearful, eye contact
good. Collaboratively updated written safety plan: warning signs,
coping steps, two contacts, 988 Suicide & Crisis Lifeline. Client
kept a copy.

ASSESSMENT
Passive suicidal ideation has increased in frequency without intent
or plan. Risk factors: worsening depressive symptoms, recent job loss.
Protective factors: lives with supportive partner, cares for dog,
engaged in treatment, future-oriented about upcoming trip. Risk
assessed as moderate per [organization's risk tool]; outpatient care
remains appropriate with safety planning.

PLAN
Increase to twice-weekly sessions for two weeks; next session
2026-11-05 10:00. Phone check-in 2026-11-03. Client agreed to call 988
or go to the nearest emergency department if intent develops. With
consent, partner will continue to keep medications. Consult with
supervisor today. Reassess risk at every contact.
The Stanley-Brown Safety Planning Intervention is a widely used structure for the written plan referenced in this example.
Example 4: Substance use, early recovery
DATA
Client reported 6 days without alcohol since last session and one
lapse on 2026-10-30 ("four beers at my brother's birthday"). Attended
2 peer support meetings. Appearance neat, alert and oriented, no signs
of intoxication. Client identified the party and arguing with brother
as triggers. Denied SI/HI. Intervention: relapse prevention, mapped
high-risk situations, rehearsed refusal statements.

ASSESSMENT
Client is maintaining progress toward the abstinence goal with one
lapse tied to a family event. Quick return to abstinence and
continued meeting attendance are strengths. Family conflict remains
the main relapse trigger.

PLAN
Weekly individual sessions; next session 2026-11-09 15:00. Continue
2 peer support meetings per week. Write a coping plan for the next
family gathering (2026-11-26) and bring it next session. With consent,
coordinate with IOP counselor about the lapse.
Example 5: Adolescent session with a parent present
DATA
Client (15) seen individually for 40 minutes, then with mother for
10 minutes. Client stated, "I stopped going to lunch because nobody
talks to me." Mother reports client spends most evenings alone in his
room and grades dropped from B to D in two classes. Client made
limited eye contact, answered in short phrases, smiled when talking
about his dog. Denied SI/HI. Intervention: social skills role-play for
starting a conversation; discussed school counselor contact with
mother.

ASSESSMENT
Social withdrawal and falling grades suggest worsening peer isolation
affecting school functioning. Client engaged in role-play and could
name one classmate he would approach. Parent is supportive and
willing to coordinate with school.

PLAN
Weekly sessions; next session 2026-11-11 16:00. Client will start one
conversation at lunch on 2 days this week. With signed release,
contact school counselor about a lunch group. Mother will track
evenings out of room. Review progress with both next session.
Example 6: Group therapy session
DATA
Group: anxiety skills group, session 4 of 8, 90 min, 7 members
present. Client participated in grounding exercise and shared one
example of using box breathing at work. Offered supportive feedback
to another member. Client stated, "Breathing helps, but I still leave
the room when my manager raises her voice." Denied SI/HI on check-in
form.

ASSESSMENT
Client is using taught skills outside group and shows good peer
engagement. Avoidance of conflict situations continues and is the
main remaining target.

PLAN
Attend session 5 on 2026-11-12. Practice box breathing before leaving
a room, and log 2 attempts to stay in place for at least 2 minutes.
Discuss workplace conflict scenario in next individual session.
In group notes, write about the client the note is for. Don't record other members' names or personal details in this client's record.
Example 7: Case management contact
DATA
Phone contact 2026-11-03, 14:00-14:20, with client. Client reported
an eviction notice dated 2026-10-28 with a court date of 2026-11-18.
Client has not applied for rental assistance. Client stated, "I
didn't know where to start." Reviewed county rental assistance and
legal aid options.

ASSESSMENT
Housing instability is an urgent barrier to treatment attendance and
stability. Client is motivated but needs help completing the
application before the court date.

PLAN
Meet in office 2026-11-05 10:00 to complete the rental assistance
application together; client will bring the notice, ID and income
proof. With consent, refer to legal aid today. Follow up by phone
2026-11-12.
DAP note template
Copy the template below into your EHR's free-text fields, a document, or a note-taking app. Change the prompts to match your organization's required fields.
SESSION HEADER
Client: [name or ID]            DOB: [date]
Date of service: [YYYY-MM-DD]   Start-stop: [00:00-00:00] ([n] min)
Service: [individual / family / group / case management]
Setting: [in person / telehealth: platform, audio+video, consent on file,
          client location, clinician location]
Participants: [client only / client + name, relationship]
Diagnosis being treated: [code, description]
Treatment plan goal addressed: [goal]

DATA
Client report and quotes: [what the client said, in their words]
Observations: [appearance, behavior, affect, speech, thought process]
Measures: [instrument = score, date; prior score, date]
Risk screen: [SI / HI / self-harm: questions asked and answers]
Interventions delivered: [methods used in this session]
Collateral / required reports: [who, when, why, consent]

ASSESSMENT
Progress toward goal: [improved / unchanged / worse, and the evidence]
Measure interpretation: [severity band and change]
Risk formulation: [risk factors, protective factors, risk level]
Functional impact: [work, school, relationships, self-care]
Need for continued care: [why this level and frequency are indicated]

PLAN
Next session: [date, time, frequency]
Interventions and target: [method; measurable goal and date]
Homework: [specific tasks the client agreed to]
Safety steps: [plan reviewed or updated, resources given]
Coordination / referrals: [who, why, consent on file]

Signature: [name, credentials]   Signed: [YYYY-MM-DD 00:00]
Download the same template: DAP note template (DOCX), printable DAP note template (PDF), or plain text (TXT). The PDF has a second page with the filled depression example from this guide.
Common DAP note mistakes
| Mistake | Why it is a problem | Fix |
|---|---|---|
| Interpretation in Data | Mixes facts with judgment and weakens the record | Move labels to Assessment and describe the behavior in Data |
| New facts in Assessment | Reviewers cannot see where the conclusion came from | Add the fact to Data first, then interpret it |
| "Client is safe" | A conclusion with no evidence behind it | Record the screening questions, answers and protective factors |
| Scores with no context | A number alone does not show change | Add the date, prior score and severity band |
| Plan says only "continue therapy" | Does not show why care is needed or what comes next | Name the interventions, homework, next date and target |
| Copy-forward text | Old symptoms or risk details may no longer be true | Re-check every carried-forward line against today's session |
| Psychotherapy note content in the progress note | Private process notes become part of the shared record | Keep personal hypotheses and process notes separate |
| Late notes | Details get lost, and some payers set completion deadlines | Finish notes the same day when possible; label late entries |
DAP vs SOAP vs BIRP vs DARP
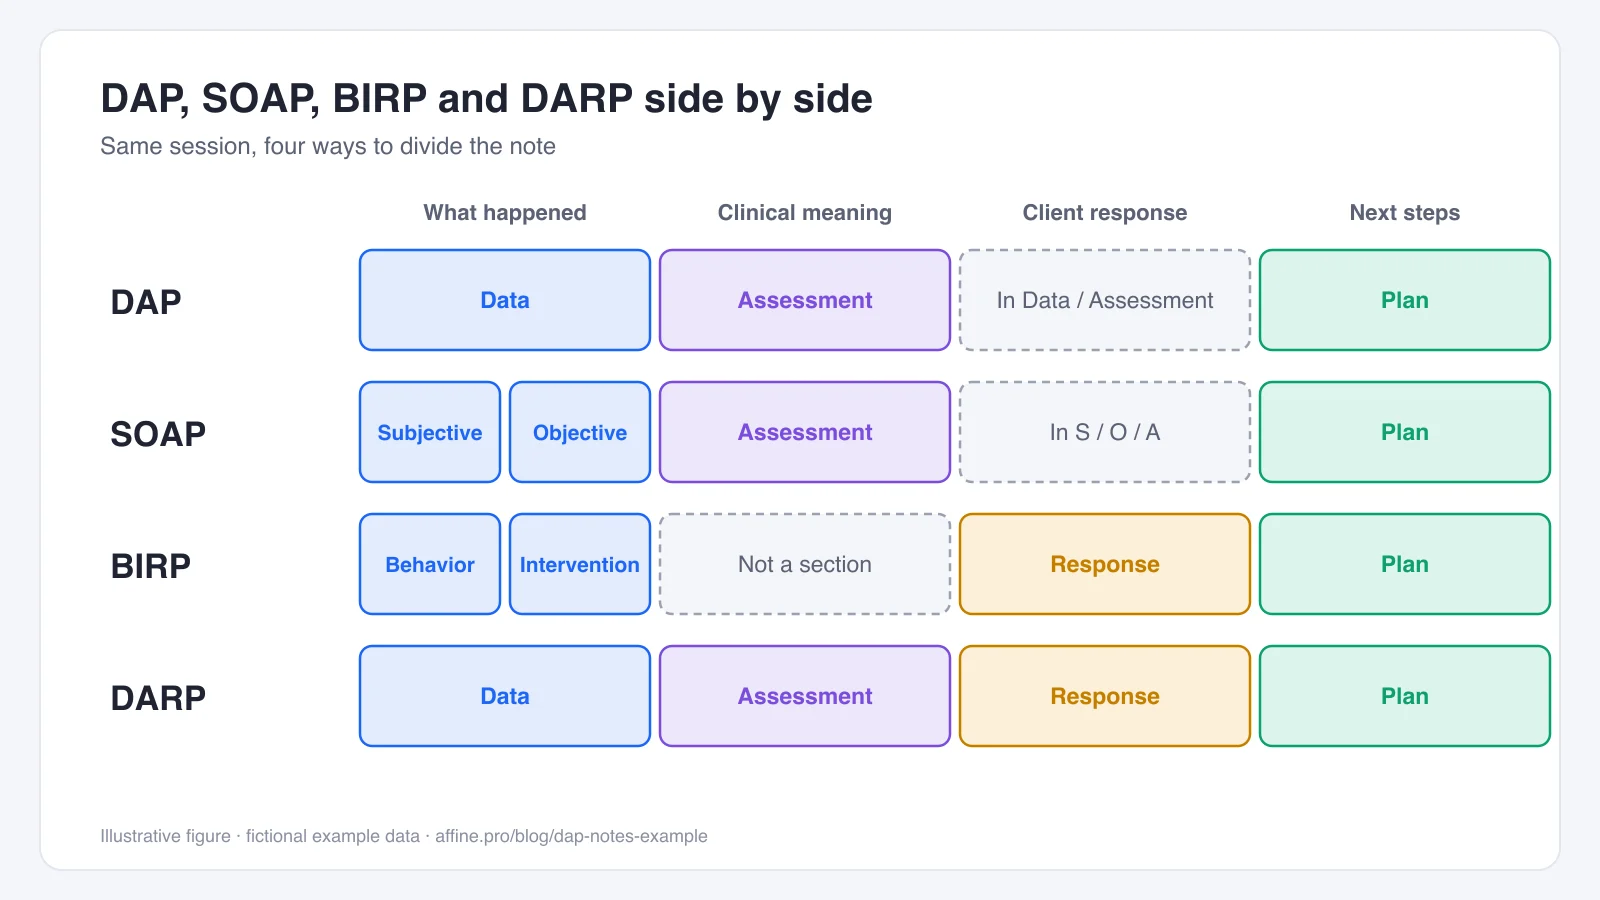
| Format | Sections | Best for | Trade-off |
|---|---|---|---|
| DAP | Data, Assessment, Plan | Ongoing therapy and counseling, case management | Requires discipline to keep Data factual |
| SOAP | Subjective, Objective, Assessment, Plan | Medical and multidisciplinary settings, intakes, complex cases | Longer; S/O split can feel forced in talk therapy |
| BIRP | Behavior, Intervention, Response, Plan | Behavior-focused programs, groups, skills training | Less room for formulation and measures |
| DARP | Data, Assessment, Response, Plan | Settings that want the client's response recorded separately | Adds a section that DAP folds into Data and Assessment |
To convert a SOAP note to DAP, merge Subjective and Objective into Data and keep Assessment and Plan as they are. To convert DAP to SOAP, split Data into what the client reported (Subjective) and what you observed or measured (Objective). For a full therapy example in SOAP format, see the therapy SOAP note example. For a side-by-side look at every progress note format, see progress notes templates compared.
DAP notes vs psychotherapy notes
A DAP note is a progress note. It becomes part of the client's record and may be shared with payers, supervisors and other providers under your organization's policies. Psychotherapy notes are different.
Under HIPAA, psychotherapy notes are a mental health professional's notes analyzing the content of a counseling session, kept separate from the rest of the record. The same definition excludes start and stop times, treatment modalities and frequency, test results, and summaries of diagnosis, functional status, treatment plan, symptoms, prognosis and progress. Those items belong in the progress note. HHS explains that disclosing psychotherapy notes generally requires the patient's authorization.
In practice: write the DAP note for the record, and keep personal hypotheses and process reflections in separate psychotherapy notes if you keep them at all. For more detail, see psychotherapy note vs progress note.
DAP note audit checklist

Before you sign, check:
- Header has the date, start and stop time, service type, setting and participants.
- Telehealth notes include modality, consent and both locations.
- Every Data sentence is a quote, an observation, a score or an action.
- Scores include the instrument, date and prior score.
- Risk screening is documented with questions and answers, not just "safe."
- Assessment interprets only what is in Data and states progress toward goals.
- Assessment explains why the current level of care is still needed.
- Every Plan item ties to something in Assessment and is specific enough to check.
- No psychotherapy-note content or other clients' details are in the record.
- The note is signed with name, credentials, date and time, and late entries are labeled.
Using AI and AFFiNE for DAP notes
Templates, phrase banks and AI can shorten documentation time, but the clinician still owns the note. If you use any AI tool, verify every fact against the session, remove anything it invented, and sign only what you would defend. Don't enter client information into a tool your organization hasn't approved for protected health information. For dedicated clinical tools, see our guides to AI scribes for therapists and ambient AI scribes.
AFFiNE is a general workspace for docs, whiteboards and databases. It is not an EHR or a clinical documentation system, and this guide does not describe it as compliant with HIPAA or any other health privacy rule. Clinicians and training programs can use it for the parts of documentation work that involve no client data:
- Template drafting. Keep a master DAP template, telehealth lines and a wording swap list in one doc, then paste the final text into your EHR.
- Training material. Build fictional example notes, like the ones in this guide, for students or new staff, with a checklist next to each.
- Template governance. Record who owns each template, when it was last reviewed, and what changed.
- Local storage. A local workspace in the AFFiNE desktop app stores docs on that device. Docs can be exported to Markdown, HTML or PDF.

DAP note FAQs
What is a DAP note?
A DAP note is a progress note format used in therapy, counseling and case management. It has three sections: Data for what happened in the session, Assessment for what it means clinically, and Plan for the next steps. Each section should follow from the one before it.
What is an example of a DAP note?
A short example: Data, "Client reported sleeping 4 to 5 hours a night; PHQ-9 = 17, up from 12; denied suicidal ideation." Assessment, "Depressive symptoms have worsened since last session." Plan, "Weekly therapy, two scheduled activities before next session, repeat PHQ-9 next week."
What goes in the Data section of a DAP note?
Data holds facts from the session: client quotes or summarized reports, observed behavior and mental status, standardized scores with dates, risk screening answers, interventions you delivered, and any collateral contacts. Interpretations and diagnoses belong in Assessment.
What is the difference between DAP and SOAP notes?
Both formats end with an Assessment and a Plan. SOAP splits session information into Subjective, what the client reports, and Objective, what you observe or measure. DAP combines both into a single Data section, which makes it shorter and well suited to talk therapy.
How long should a DAP note be?
Most routine DAP notes run from a short paragraph to about half a page per section. Length matters less than completeness: the note needs enough Data to support the Assessment and a Plan specific enough for another clinician to follow. Crisis and intake notes are usually longer.
Are DAP notes the same as psychotherapy notes?
No. A DAP note is a progress note that is part of the client's record. Psychotherapy notes are a clinician's separate notes analyzing session content. HIPAA defines them narrowly and excludes session times, test results, diagnosis and treatment plan summaries, which belong in the progress note.
Sources and review notes
This guide combines and replaces two earlier AFFiNE articles on DAP notes. It was rewritten on November 4, 2026, as a documentation guide, not a clinical protocol. The definitions and score bands were checked against the primary sources below. All example notes are fictional. The guide has not been reviewed by a licensed clinician, so check it against your supervisor's guidance, payer manuals and licensing board rules before you change your documentation. AFFiNE's fact-checking and correction standards are in our editorial policy.
- 45 CFR 164.501, definition of psychotherapy notes (eCFR)
- HHS: Does HIPAA provide extra protections for mental health information?
- Kroenke K, Spitzer RL, Williams JB. The PHQ-9: validity of a brief depression severity measure. J Gen Intern Med, 2001
- Spitzer RL et al. A brief measure for assessing generalized anxiety disorder: the GAD-7. Arch Intern Med, 2006
- CMS: Medicare telehealth services
- Stanley-Brown Safety Planning Intervention
- 988 Suicide & Crisis Lifeline
- AFFiNE docs: local and cloud workspaces